

When Medication Isn’t the Only Answer.
A non-invasive, FDA-cleared treatment that uses focused magnetic pulses to stimulate a specific region of the brain. You stay awake, there is no anesthesia or sedation, and it is generally well tolerated.
Talk With Our Team
Ask whether TMS makes sense for you. We will call you back.
Talk With Our Team
Ask whether TMS makes sense for you. We will call you back.
What TMS Actually Is
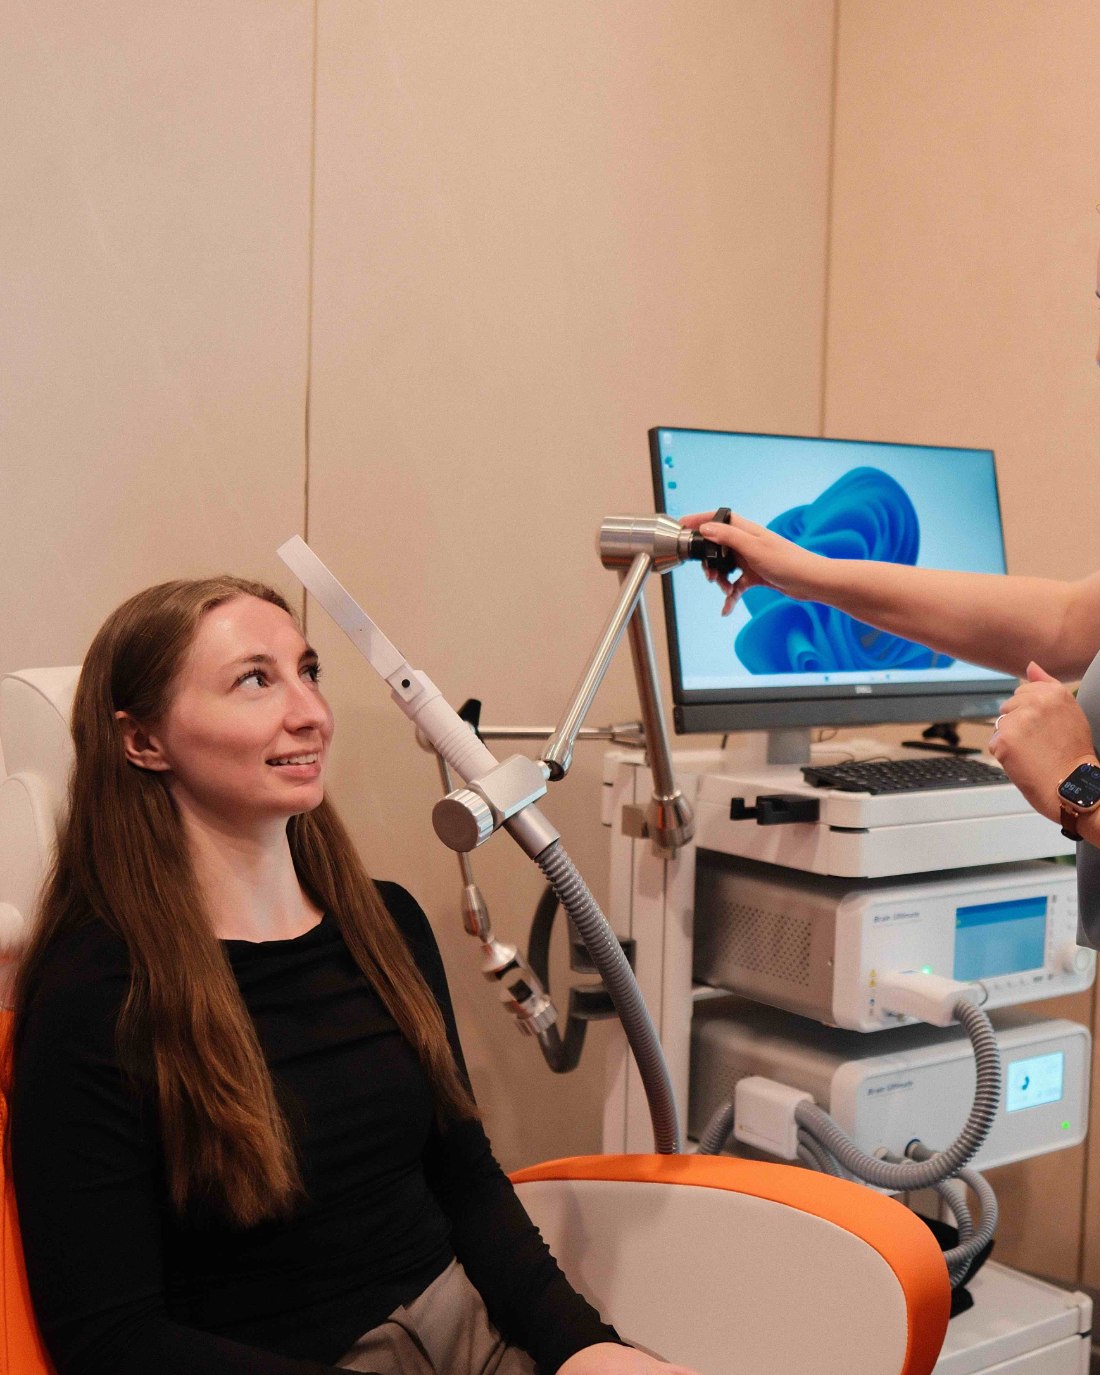
You sit in a comfortable chair, awake and conversational, while a coil rests gently against your head and sends subtle magnetic pulses — the same class of magnetic field used in an MRI — to the areas of the brain involved in mood regulation.
Most people describe two things: an odd tapping sensation on the scalp, and a machine that is noisier than they expected. Neither one stops the conversation. When the session ends, you stand up and get on with your day.
There is nothing to endure and nothing to recover from. It is a steady, targeted nudge to a circuit that has gone quiet — repeated often enough that the change has a chance to hold.
Activity, Not Personality
In depression, activity in certain regions of the brain is measurably reduced. That is not a character flaw or a failure of effort — it is a pattern of activity. TMS targets that pattern directly.
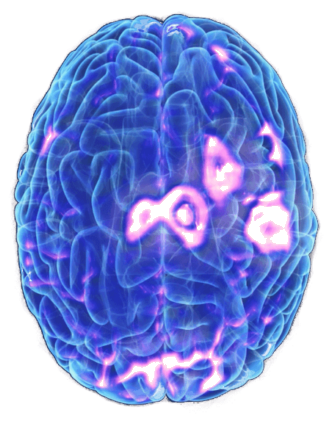
Electrical activity in certain areas of the brain is reduced. Concentration, motivation, and mood regulation all run on those circuits.
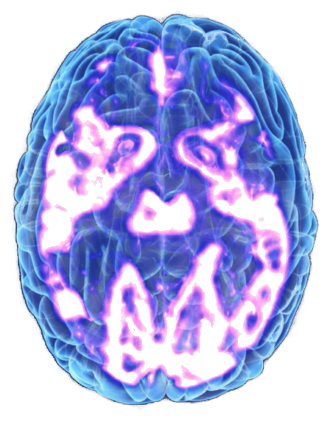
After a completed course, activity in those same regions can increase. The aim is to restore function in the circuit, not to alter who you are.
Illustrative images based on PET scans. They show the mechanism TMS targets, not a prediction of any individual result.

Biology First, Then the Work
Our model is built on four pillars, in order: stability, capacity, regulation, ownership. Therapy asks the brain to attend, remember, tolerate discomfort, and choose differently — and if the biology cannot support that, the insight does not stick, no matter how good the therapy is.
TMS is not one of those pillars. It is acceleration — the channel that runs above them, sloped so that what is in it keeps moving. It does not replace a pillar and it cannot stand without them, but when it is clinically appropriate it makes the work flow more naturally instead of being pushed uphill, and it gives capacity more to draw on.
This is also why we never offer it alone. TMS inside a program that includes therapy, movement, psychiatry, sleep, and family work is a very different proposition from TMS as a standalone appointment.
An aqueduct slopes gently downhill so the water carries itself. The pillars are built in order and hold the weight; acceleration is the channel they carry, and the slope is what makes the flow natural instead of forced. It moves the work along under its own momentum — and it has nothing to stand on without the pillars. Illustrative.
TMS Is a Bit Like Jump-Starting a Car
It can get the system moving again, and it is a genuinely powerful tool. However, a jump-start does not fix the reason the battery died in the first place.
Magnetic pulses into a targeted region, repeated across a course. Circuits that had gone quiet can start participating again, and what felt impossible gets closer to possible.
Sleep, labs and thyroid, medication, nutrition, movement, grief, what is happening at home, what happens when treatment ends. If nobody looks there, only one part of the picture has been addressed.
What the Sessions Look Like
TMS is not a program of its own — it fits into one. It runs as a course of sessions over several weeks, and the repetition is the active ingredient.
A psychiatric evaluation and medical review: your diagnosis, what you have already tried, your medications, and any reason TMS would not be safe for you.
At the first session we locate your motor threshold and map the coil position for your head. Dose is set from your own physiology, not an average.
A typical course runs 30 to 36 sessions across several weeks. You sit, the coil clicks, you leave. Most people fit them around work or before program hours.
Standardized symptom measures at intervals, not just "how do you feel." If nothing is moving by the expected point, we say so and reconsider.
Frequency, session count, length, and protocol depend on the device, your diagnosis, and your insurance authorization. Your psychiatrist will give you the specific plan in writing.
Where It Fits for You
We do not treat TMS as a last resort, and we do not think of it as what you try once medication has not worked — we would rather do everything we can before medication becomes the centre of a plan at all. The question we ask is the same one we ask about everything: is the biology able to support the work being asked of it, and would this help it get there? Sometimes that answer comes early.
That said, it is not right for everyone, and we would rather find that out before you start than after. A seizure history, or certain implanted metal or devices in the head, can make TMS unsafe, so screening happens first — always before anything is scheduled. Insurers also tend to ask for a record of what you have already tried. That is a billing requirement rather than our clinical opinion, and we will help you put it together.

And the Part That Is Different Here
Most plans want several medication trials documented first — often months of them.
A course runs 30 to 36 sessions. Uncovered, that is thousands out of pocket.
A denial does not have to be the end of it. For PHP and IOP patients who clinically qualify, TMS is included in the program at no additional cost.
Any copay, coinsurance, or deductible your plan requires still applies — we are required to collect it. We verify your benefits first and tell you the number before you start.
Eligibility is determined by our clinical team, not by your coverage.
TMS Is Not the Treatment Plan. It Is Part of One.
Almost everywhere else, TMS is a standalone service. Your TMS provider, your therapist, your psychiatrist, your primary care provider — four people who may never speak to each other, and you carrying the messages between them.
One team. One coordinated program. One record — when TMS is clinically appropriate.

TMS Is Not Electroconvulsive Therapy
This is the single most common fear people arrive with, so it is worth being blunt about the difference.

One Instrument in a Larger Plan
TMS raises capacity. It does not teach a skill, repair a relationship, rebuild a sleep schedule, or change what happens at home. That is what the rest of the program is for.
The combination is the point. When the circuit has more to give and the same week also contains therapy, movement, group work, and family sessions, the gains have somewhere to go.
Frequently Asked Questions


Come See the Whole Place — Not Just the TMS Chair
Bring your history, your medication list, and your questions. Book a free tour and consultation, and a clinical team will tell you honestly whether TMS belongs in your plan.